
For decades, the medical establishment has evaluated metabolic health through a profoundly flawed, overly simplistic lens. We rely on fasting glucose—a single, static snapshot taken at 8:00 AM after a 12-hour fast—and HbA1c, which provides a three-month rolling average of blood sugar. But in systems biology, averages are the refuge of the biologically blind. An average tells you nothing about the volatility of the system. You could have an HbA1c of 5.2% because your blood sugar sits at a perfectly stable 95 mg/dL all day, or you could have an HbA1c of 5.2% because your blood sugar violently swings between 60 mg/dL and 180 mg/dL every time you eat.
The latter scenario is the silent epidemic of the modern world. This is glycemic variability (GV). It is the metabolic rollercoaster. And while your HbA1c might look pristine on your annual lab report, the violent excursions of your daily glucose curve are actively generating oxidative stress, accelerating vascular aging, and driving the neuroinflammation that manifests as the dreaded 2:00 PM brain fog.
As a strategist focused on the “Food as Information” movement, I view every meal not just as caloric fuel, but as a hormonal and epigenetic signal. When you subject your vascular system to extreme glycemic volatility, you are sending a signal of metabolic chaos. Let’s dismantle the dogma of the “normal” blood test and map the precise biochemical reality of glycemic variability, the tools required to measure it, and the exact protocols needed to flatten your curve and engineer profound metabolic resilience.
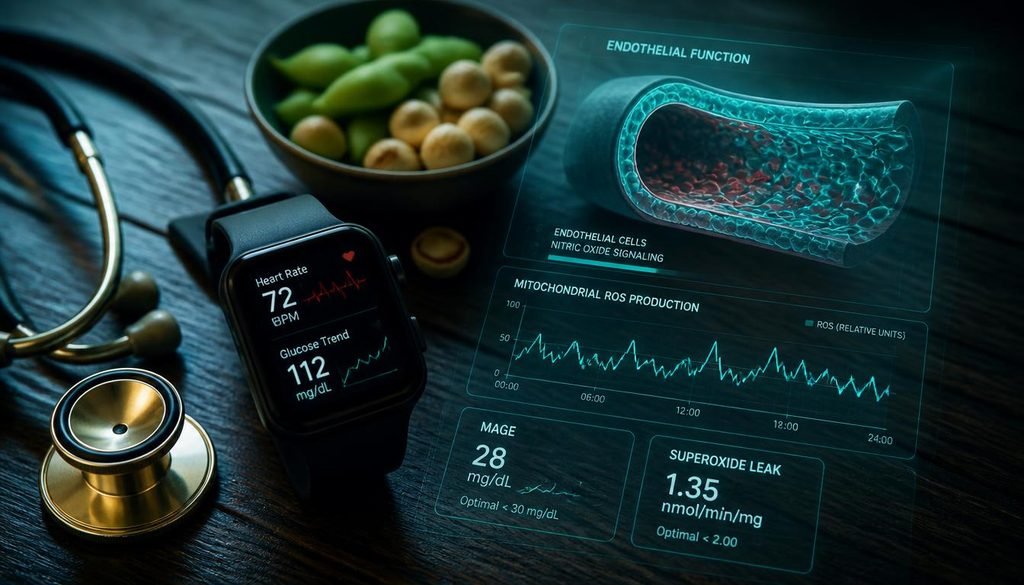
Glycemic variability normal range
To optimize a biological system, you must first define the parameters of success. The glycemic variability normal range is not determined by how high your glucose goes, but by the mathematical dispersion of your data points around your mean glucose level.
In clinical endocrinology, the gold standard metric for measuring this dispersion is the Coefficient of Variation (CV%). The CV is calculated by dividing the standard deviation of your glucose readings by your mean glucose, then multiplying by 100. It essentially tells you how “bouncy” your blood sugar is relative to your baseline.
The Clinical vs. Optimal Thresholds
- The Clinical Standard: The American Diabetes Association (ADA) and major endocrinology consensus guidelines generally define a “stable” glycemic variability as a CV of less than 36%. If your CV is below 36%, your glucose fluctuations are considered clinically manageable, and your risk of acute hypoglycemic events is relatively low.
- The Longevity Optimal: A CV of 35% is merely the threshold for avoiding acute diabetic crises; it is not the threshold for biological optimization. For a metabolically flexible, high-performing adult, the target CV should be strictly below 25%, and ideally hovering between 15% and 20%.
When your CV is below 20%, your blood sugar behaves like a gentle, rolling hill rather than a jagged mountain range. Your mitochondria are receiving a steady, predictable stream of pyruvate, your endothelium is protected from oxidative shear stress, and your brain is spared the neurochemical whiplash of reactive insulin surges.
Glycemic variability in non diabetics
The most dangerous myth in modern medicine is that glycemic volatility is exclusively a diabetic concern. The reality of glycemic variability in non diabetics is a hidden driver of accelerated aging, chronic fatigue, and endothelial dysfunction in seemingly “healthy” individuals.
The Postprandial Oxidative Storm
When a metabolically “normal” person consumes a highly processed, carbohydrate-dense meal (like a bowl of oatmeal with maple syrup or a plate of pasta), their blood glucose can easily spike to 140 mg/dL or 160 mg/dL, before crashing back down to 80 mg/dL two hours later.
This rapid spike floods the mitochondria in your endothelial cells (the cells lining your blood vessels) with excess metabolic substrates. The electron transport chain backs up. Electrons leak out and bind to oxygen, creating a massive burst of superoxide—the primary reactive oxygen species (ROS). According to foundational metabolic research published by the National Institute of Diabetes and Digestive and Kidney Diseases (NIH), it is not chronic, stable high blood sugar that causes the most acute vascular damage; it is the rapid oscillation of glucose. These acute spikes trigger the activation of Protein Kinase C (PKC) and the production of Advanced Glycation End-products (AGEs), which physically cross-link with collagen in your arteries, stripping them of their elasticity.
The Visceral Fat Connection
Why do non-diabetics experience these massive spikes? Often, it is driven by hidden visceral adiposity. Visceral fat pumps out inflammatory cytokines (like TNF-alpha) that induce localized insulin resistance in the liver and muscle tissue. When your muscles refuse to pull glucose out of the blood efficiently, the glucose lingers, spikes, and eventually forces the pancreas to over-secrete insulin, leading to the inevitable crash. To ensure your internal inflammatory environment isn’t driving your glycemic volatility, track your true metabolic risk using our Advanced BMI Calculator and our Body Fat Calculator to identify and eliminate central adiposity.
Glycemic variability index
To truly master your metabolic data, you must understand the glycemic variability index and the specific mathematical models used to quantify it. Relying solely on standard deviation is insufficient because standard deviation scales with the mean; a person with a higher average glucose will naturally have a higher standard deviation, even if their relative volatility is the same.
1. Coefficient of Variation (CV%)
As established, CV% is the most robust metric for overall stability. It normalizes the standard deviation against the mean, providing a true percentage of volatility. This is the primary metric displayed on modern Continuous Glucose Monitor (CGM) dashboards.
2. Mean Amplitude of Glycemic Excursions (MAGE)
While CV% looks at the overall spread of the data, MAGE looks specifically at the magnitude of the peaks and valleys. MAGE calculates the average difference between consecutive peaks and nadirs (the highest and lowest points of a glucose swing) that exceed one standard deviation.
- Why it matters: You could have a relatively tight CV, but if you experience one massive, 80-point spike every day after dinner, your MAGE will be high. MAGE is heavily correlated with postprandial oxidative stress and the subjective feeling of the “afternoon crash.” An optimal MAGE for a non-diabetic is generally less than 40 mg/dL to 50 mg/dL.
3. Time in Range (TIR) and Time in Tight Range (TITR)
While not strictly a variability index, TIR (the percentage of time spent between 70-140 mg/dL) and the more stringent TITR (70-110 mg/dL) are the ultimate functional outputs of low glycemic variability. If your CV is low and your MAGE is low, your TITR will naturally approach 90% or higher. The American Diabetes Association (ADA) increasingly emphasizes TIR over HbA1c for capturing the true daily reality of glycemic control.
Glycemic variability in diabetes
When we transition from optimization to pathology, glycemic variability in diabetes becomes a primary driver of the microvascular and macrovascular complications that define the disease.
The “Legacy Effect” and Endothelial Apoptosis
In type 1 and type 2 diabetes, high glycemic variability is far more destructive than stable hyperglycemia. Landmark clinical trials have demonstrated that patients with high GV exhibit significantly higher rates of retinopathy, nephropathy, and neuropathy, even when their HbA1c is matched with patients who have stable, but chronically elevated, blood sugar.
The biochemical mechanism is ruthless. Rapid glucose fluctuations trigger “endothelial apoptosis”—the programmed cell death of the cells lining your blood vessels. Furthermore, high GV induces a phenomenon known as “metabolic memory” or the “legacy effect.” The oxidative stress generated by a week of highly variable blood sugar alters the epigenetic expression of inflammatory genes, and this inflammatory state persists for months, even after the glucose levels are stabilized.
The Hypoglycemic Danger Zone
For diabetics on insulin or sulfonylureas, high GV is also a massive safety risk. A high CV% means the patient is experiencing wild swings, drastically increasing the frequency and severity of hypoglycemic events (blood sugar dropping below 70 mg/dL). Severe hypoglycemia triggers a massive sympathetic nervous system response, dumping adrenaline and cortisol, which can induce fatal cardiac arrhythmias or seizures. Flattening the curve is not just about longevity for diabetics; it is about immediate survival.
Glycemic variability causes
If you are experiencing massive glucose swings, it is rarely just about “eating too much sugar.” The glycemic variability causes are deeply rooted in your behavioral architecture, your circadian biology, and your microbial ecosystem.
1. Naked Carbohydrates and Food Sequencing
Consuming carbohydrates on an empty stomach, without the buffer of fiber, protein, or fat, leads to rapid gastric emptying. The glucose hits the small intestine all at once, causing a massive, immediate absorption spike.
2. Circadian Misalignment and Late Eating
Your pancreas and skeletal muscle are highly circadian. Insulin sensitivity peaks in the morning and plummets in the evening. If you consume 50 grams of carbohydrates at 8:00 AM, your muscles efficiently clear it. If you consume the exact same 50 grams at 9:00 PM, your pancreas must secrete vastly more insulin to force the glucose into the cells, leading to a delayed, prolonged spike and a severe nocturnal crash that fragments your sleep architecture. Align your eating windows with your biological clock using our Intermittent Fasting Calculator.
3. Sleep Deprivation and Cortisol
A single night of fragmented or insufficient sleep can reduce whole-body insulin sensitivity by up to 30% the following day. Sleep deprivation keeps the sympathetic nervous system activated, elevating baseline cortisol. Cortisol actively stimulates hepatic gluconeogenesis (the liver dumping stored glucose into the blood), creating a high, volatile baseline that makes every meal spike higher than it normally would.
4. Microbiome Dysbiosis and Incretin Failure
Your gut microbiome dictates the release of GLP-1 and GIP—the incretin hormones that signal the pancreas to release insulin before glucose even enters the bloodstream. If your microbiome is degraded by emulsifiers, antibiotics, or a lack of fermentable fibers, your incretin response is blunted. The pancreas is caught off guard, insulin is delayed, and the glucose spike is magnified. Rewilding your gut ecosystem with targeted prebiotics and next-generation keystone species is critical for blunting these excursions. (For a deep dive into rebuilding this ecosystem, read our protocol on Next-Gen Probiotics: Rewilding the Internal Ecosystem).
Glycemic variability symptoms
You do not need a continuous glucose monitor to feel the effects of a volatile metabolic environment. The glycemic variability symptoms manifest across multiple physiological systems, often misdiagnosed as simple stress or aging.
1. The Post-Prandial Crash (Reactive Hypoglycemia)
The most obvious symptom is the 2:00 PM energy collapse. After a massive glucose spike, the pancreas over-secretes insulin to clear the blood. This drives glucose down so rapidly that it overshoots the baseline, dropping into reactive hypoglycemia (often below 70 mg/dL). The brain, sensing an energy crisis, triggers an adrenaline dump to force the liver to release stored glycogen. This adrenaline surge causes the physical symptoms: tremors, anxiety, irritability (“hangry”), and profound fatigue.
2. Neuroglycopenia and Brain Fog
The brain relies almost exclusively on glucose for fuel, but it requires a steady stream. When glycemic variability is high, the rapid shifts in blood glucose disrupt the blood-brain barrier’s transport mechanisms. The resulting neuroglycopenia (a localized shortage of glucose in the brain) manifests as an inability to concentrate, poor working memory, and a feeling of mental heaviness.
3. Endothelial Dysfunction and Cold Extremities
Because acute glucose spikes generate massive amounts of superoxide in the endothelium, they temporarily neutralize nitric oxide (NO). Without NO, your blood vessels cannot dilate properly. If you experience cold hands and feet, or transient erectile dysfunction immediately following a heavy, carbohydrate-rich meal, you are experiencing acute, GV-induced endothelial dysfunction.
4. Nocturnal Awakenings
If your blood sugar crashes rapidly in the middle of the night due to a late, high-carbohydrate dinner or an alcohol-induced rebound, the resulting adrenaline and cortisol spike will jolt you awake, typically between 2:00 AM and 3:00 AM, with a racing heart and a racing mind.
Glycemic variability cgm
The commercialization of the glycemic variability cgm (Continuous Glucose Monitor) has fundamentally altered the biohacking and longevity landscape. Devices like the Dexcom G7 and Abbott FreeStyle Libre 3 allow non-diabetics to see their metabolic data in real-time, transforming an invisible physiological process into actionable data.
The Power of the N=1 Experiment
A CGM reveals the profound individuality of human metabolism. A banana might cause a massive 60-point spike in one person, while a bowl of white rice leaves their curve perfectly flat. Genetics, microbiome composition, and baseline muscle mass dictate these responses. Wearing a CGM for 14 to 30 days allows you to build a personalized “glycemic fingerprint,” identifying the specific foods, meal times, and stressors that disrupt your unique biology.
The Pitfall of Orthorexia and Cortisol Obsession
However, the CGM comes with a severe psychological caveat. Staring at your glucose data every five minutes can trigger orthorexia—an unhealthy obsession with “perfect” numbers. Furthermore, the anxiety of watching your glucose rise after a meal triggers a sympathetic nervous system response, dumping cortisol, which actually drives your blood sugar higher.
The Protocol: Wear the CGM for one month to learn your body’s responses. Test food sequencing, test walking after meals, and test fasting windows. Once you have built a mental database of how your body responds to specific inputs, take the sensor off. Rely on your internal biofeedback—your energy, your mood, and your hunger signals—rather than becoming permanently tethered to a digital readout.
💡 Action Step: To ensure your muscles are primed to act as a massive glucose sink, blunting post-prandial spikes naturally, you must maintain high metabolic flexibility. Calculate your exact daily energy expenditure with our TDEE Calculator and ensure you are preserving your lean muscle mass by hitting your daily targets via our Protein Intake Calculator.
Glycemic variability treatment
Flattening your glucose curve does not require a zero-carbohydrate diet. It requires strategic behavioral and biochemical interventions that slow gastric emptying, enhance insulin sensitivity, and optimize cellular glucose disposal. The glycemic variability treatment protocol relies on four foundational pillars.
1. Food Sequencing (The “Clothing” Protocol)
Never eat a “naked” carbohydrate. The order in which you consume the macronutrients on your plate drastically alters the glycemic response.
- The Protocol: Eat your fiber (vegetables) first. Eat your protein and fats second. Eat your complex carbohydrates last.
- The Mechanism: Fiber creates a physical mesh in the small intestine, slowing the absorption of glucose. Protein and fat trigger the release of cholecystokinin (CCK) and GLP-1, which slow gastric emptying and prime the pancreas for a measured, rather than panicked, insulin release. Clinical data shows that simply changing the order of food consumption can reduce the post-prandial glucose spike by up to 40%.
2. Post-Prandial Mechanical Disposal
Skeletal muscle is the largest glucose sink in the human body. When you contract a muscle, it triggers the translocation of GLUT4 receptors to the cell surface, pulling glucose out of the bloodstream without requiring insulin.
- The Protocol: Never sit down immediately after a meal. Engage in 10 to 15 minutes of light movement—a brisk walk, doing the dishes, or bodyweight squats. This mechanical contraction acts as a biological sponge, soaking up the circulating glucose and blunting the peak. For a comprehensive guide to building your metabolic engine, read our protocol on Zone 2 Cardio: The Mitochondrial Engine of a Longer Healthspan.
3. Botanical and Acidic Buffers
You can utilize specific compounds to chemically blunt the enzymatic breakdown of carbohydrates in the gut.
- Acetic Acid (Apple Cider Vinegar): Consuming 1 tablespoon of ACV in a tall glass of water 15 minutes before a meal inhibits alpha-amylase, the enzyme that breaks down starches into glucose, slowing the absorption rate.
- Berberine and Mulberry Leaf: These botanical compounds act as mild alpha-glucosidase inhibitors and AMPK activators, mimicking the effects of pharmaceutical glucose-disposal agents without the side effects.
- Ceylon Cinnamon: Adding true Ceylon cinnamon to your meals enhances insulin receptor sensitivity, allowing the cells to clear glucose more efficiently.
4. Circadian Fasting and the Dawn Phenomenon
Your liver naturally dumps glucose into the bloodstream in the early morning to wake you up (the Dawn Phenomenon). If you eat immediately upon waking, you stack dietary glucose on top of this hepatic dump, creating a massive morning spike.
- The Protocol: Delay your first meal by 90 to 120 minutes after waking. Allow the morning cortisol pulse to clear, let your body utilize the hepatic glucose dump, and break your fast with a high-protein, high-fat meal to maintain a flat, stable baseline for the rest of the day.
Final Thoughts
Glycemic variability is the ultimate biomarker of metabolic friction. It is the physical manifestation of a biological system struggling to process the modern environmental inputs it was never designed to handle. When you allow your blood sugar to swing violently, you are subjecting your endothelium to oxidative shear stress, your brain to neurochemical chaos, and your mitochondria to an unsustainable substrate overload.
But by shifting your focus from the static averages of HbA1c to the dynamic volatility of the daily curve, you take total control of your metabolic destiny. By sequencing your food, leveraging mechanical glucose disposal, and respecting your circadian biology, you transform your blood sugar from a chaotic rollercoaster into a smooth, efficient cruise. Flatten the curve, protect your endothelium, and engineer a biological terrain defined by unyielding stability and profound resilience.
Frequently Asked Questions (FAQ)
1. What is a normal glycemic variability range?
Glycemic variability is measured using the Coefficient of Variation (CV%). Clinically, a CV of less than 36% is considered stable for diabetics. However, for optimal longevity and metabolic health in non-diabetics, the target CV should be strictly below 25%, and ideally between 15% and 20%.
2. Why is glycemic variability dangerous for non-diabetics?
Even in non-diabetics, high glycemic variability causes acute oxidative stress. Rapid glucose spikes flood the mitochondria in the blood vessels, generating reactive oxygen species (ROS) that damage the endothelium, accelerate arterial stiffness, and drive the neuroinflammation responsible for brain fog and fatigue.
3. What are the symptoms of high glycemic variability?
The most common glycemic variability symptoms include the “afternoon crash” (reactive hypoglycemia), severe brain fog, irritability, cold hands and feet (due to acute endothelial dysfunction), and waking up between 2 AM and 3 AM with a racing heart due to nocturnal adrenaline dumps.
4. How do I calculate my glycemic variability index?
The most common glycemic variability index is the Coefficient of Variation (CV%), calculated by dividing the standard deviation of your glucose readings by your mean glucose, then multiplying by 100. Another metric is MAGE (Mean Amplitude of Glycemic Excursions), which measures the average size of your major glucose peaks and valleys.
5. What is the fastest way to reduce a glucose spike after eating?
The fastest way to blunt a post-prandial glucose spike is through mechanical disposal: taking a brisk 10 to 15-minute walk immediately after eating. Muscle contraction forces GLUT4 receptors to the cell surface, pulling glucose out of the bloodstream without requiring insulin. Additionally, consuming apple cider vinegar or fiber before the meal slows gastric emptying.
⚕️ Editorial & Medical Disclaimer
Julian Vance is not a licensed physician or medical professional. All content published on RegenStep.com is thoroughly reviewed against cited primary sources and peer-reviewed literature for educational and informational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare provider or doctor regarding any personal health condition or medical decisions, particularly before altering your diet, utilizing continuous glucose monitors, or introducing botanical supplements like berberine, especially if you are taking prescription glucose-lowering medications.

Julian Vance is the writer and editor behind RegenStep, translating peer-reviewed longevity, metabolic, and gut-health research into practical, actionable guides. Julian is not a licensed physician; content is reviewed against cited primary sources and is for informational purposes only. Always consult a qualified healthcare provider for personal medical advice.